



Laryngeal cancer symptoms: When persistent hoarseness needs medical care
Hoarseness lasting over three weeks, difficulty swallowing, persistent throat pain and a neck lump may require evaluation for laryngeal cancer.

By Bilge Türk | MediCenter TV
ANKARA, TÜRKİYE — Hoarseness lasting longer than three weeks, difficulty swallowing, persistent throat pain or an unexplained neck lump can be warning signs that warrant an ear, nose and throat examination.
Most cases of hoarseness and throat discomfort are caused by non-cancerous conditions, including respiratory infections, reflux or vocal strain. However, symptoms that persist, worsen or occur together should not be ignored.
Laryngeal cancer develops in the tissues of the larynx, commonly known as the voice box. The larynx contains the vocal cords and plays an important role in speaking, breathing and protecting the airway during swallowing.
The symptoms can vary according to the location and size of the tumour. Professor Murat Topdağ, MD, an ear, nose and throat specialist whose clinical fields include head and neck surgery, emphasises the importance of timely assessment when potentially concerning symptoms persist.

Why persistent hoarseness matters
Hoarseness is among the most frequently reported symptoms of cancers that develop on or near the vocal cords. A tumour affecting the vibration of the vocal cords may cause the voice to become rough, weak, strained, deeper or noticeably different from its usual tone.
Hoarseness is common and does not necessarily indicate cancer. Upper respiratory tract infections, allergies, reflux, benign vocal cord lesions and prolonged or forceful use of the voice can all produce similar changes.
A voice change that lasts longer than three weeks without clear improvement should nevertheless be assessed by an ENT specialist. Earlier evaluation may be particularly important for people who smoke or have smoked in the past.
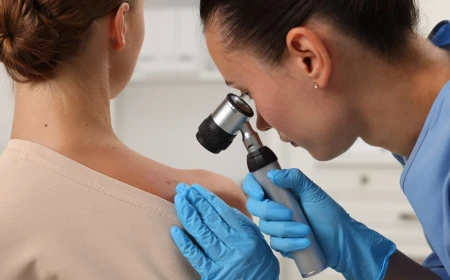
Persistent hoarseness should not automatically be attributed to smoking, ageing or frequent voice use. During an examination, the vocal cords and surrounding structures can be viewed with a thin flexible or rigid endoscope to help identify the cause.


Difficulty swallowing and persistent throat pain
Tumours located above the vocal cords or close to the swallowing passage may initially cause swallowing-related symptoms rather than an obvious change in the voice.
Patients may experience pain when swallowing, the sensation that food is becoming stuck, difficulty swallowing solid foods or a persistent feeling that something is lodged in the throat. These symptoms may gradually become more noticeable as the condition progresses.
Persistent throat pain also requires attention, particularly when it worsens during swallowing or occurs alongside voice changes, unexplained weight loss or reduced food intake.
Infections, reflux and several non-cancerous throat conditions may cause the same complaints. Symptoms alone cannot confirm laryngeal cancer, so a clinical examination is needed to determine their underlying cause.
Ear pain and neck swelling should not be overlooked
In some people, a disorder originating in the throat or larynx may be felt as pain in one ear even when an ear examination does not reveal a local problem. This is known as referred pain and occurs because parts of the ear and throat share nerve pathways.
Persistent pain affecting one ear, especially when accompanied by swallowing difficulty, throat discomfort or voice changes, may require examination of the throat and larynx.
A lump or swelling in the neck can have many causes, including infection and benign thyroid or salivary gland conditions. In some cases, however, it may indicate involvement of a lymph node.
A neck lump that grows, feels unusually firm, does not resolve or cannot be explained by a recent infection should be assessed without delay. Its duration, location and associated symptoms can help guide the diagnostic process.
Tobacco and alcohol increase the risk
Tobacco use is one of the leading risk factors associated with laryngeal cancer. Carcinogenic substances in cigarette smoke and other tobacco products can cause cellular damage in the tissues of the larynx over time.
Heavy alcohol consumption is another recognised risk factor. Using tobacco and alcohol together is associated with a greater risk than exposure to either substance alone.
Laryngeal cancer is not limited to people who smoke or consume alcohol. The disease can also develop in individuals without these known risk factors. Persistent symptoms should therefore be evaluated according to their duration and clinical characteristics, rather than lifestyle history alone.
Stopping tobacco use can reduce future cancer risk and may also support treatment outcomes in people who have already been diagnosed. Avoiding tobacco exposure remains one of the most important preventive measures for cancers of the larynx and other parts of the head and neck.
How laryngeal cancer is diagnosed
The diagnostic process usually begins with a detailed review of the patient’s symptoms, smoking and alcohol history, previous medical conditions and any recent changes in swallowing, breathing or body weight.
An ENT specialist then examines the mouth, throat, neck and larynx. Flexible or rigid endoscopy may be used to view the vocal cords and other parts of the voice box.
Seeing an abnormal area during the examination does not by itself establish a cancer diagnosis. If suspicious tissue is identified, a biopsy may be needed. The tissue sample is examined by a pathologist to determine whether cancer cells are present.
If cancer is confirmed, computed tomography, magnetic resonance imaging, ultrasound or other imaging tests may be used to assess the size and location of the tumour and determine whether nearby lymph nodes or other structures are affected.
These findings are used to establish the stage of the disease and guide an individual treatment plan.
Treatment considers voice, swallowing and breathing
Treatment depends on the tumour’s location and size, the stage of the disease, lymph node involvement and the patient’s general health.
For some early-stage tumours, options may include endoscopic or laser surgery, an operation that removes only the affected part of the larynx, or radiotherapy. When medically appropriate, these approaches may help preserve the patient’s natural voice and swallowing function.
More advanced disease may require extensive surgery, radiotherapy, chemotherapy or other systemic treatments, either separately or in combination. The most suitable approach is determined individually.
In certain cases, removal of the entire larynx may be necessary to control the disease. After a total laryngectomy, the patient breathes through a permanent opening in the neck. Voice rehabilitation methods can then be considered to restore the ability to communicate.
Because the larynx is essential for speaking, breathing and swallowing, treatment planning aims to control the tumour while preserving function and quality of life whenever possible. Care may involve specialists in ENT and head and neck surgery, medical oncology, radiation oncology, pathology, speech therapy, nutrition and rehabilitation.
Not every episode of hoarseness or throat pain is a sign of cancer. However, a voice change lasting longer than three weeks, persistent swallowing difficulty, unexplained one-sided ear pain or a neck lump should not be ignored.
Marked difficulty breathing, noisy breathing or a rapidly worsening airway problem requires urgent medical assessment.
MediCenterTV.com
 Like
0
 Dislike
0
 Love
0
 Funny
0
 Wow
0
 Sad
0
 Angry
0

Bilge Türk, MediCenterTV.com editörü, gazeteci ve yazardır. Sağlık, yaşam, bilim ve güncel gelişmeler üzerine içerikler hazırlayan Türk; doğru, anlaşılır ve toplum yararını gözeten habercilik anlayışıyla sağlık alanındaki gelişmeleri okuyuculara aktarmayı amaçlamaktadır.














Comments (0)